Male pattern hair loss (MPHL), also known as androgenetic alopecia, is the most common form of hair loss in men. It is a progressive condition influenced by genetic predisposition, androgen activity, and age.
This page provides general information about the biology, clinical features, and management options for MPHL. It is for educational purposes only and is not medical advice. Treatment decisions require an individual assessment by a registered medical practitioner.
Contact Us via WhatsApp

The biological mechanisms behind Male Pattern Hair Loss
The term androgenetic alopecia reflects interacting androgenic and inherited factors. Testosterone is converted to dihydrotestosterone (DHT) by 5-alpha reductase. In genetically susceptible scalp follicles, DHT is associated with a shorter anagen (growth) phase and progressive follicular miniaturisation. Successive cycles may therefore produce shorter, finer, less pigmented hairs until visible growth is reduced.
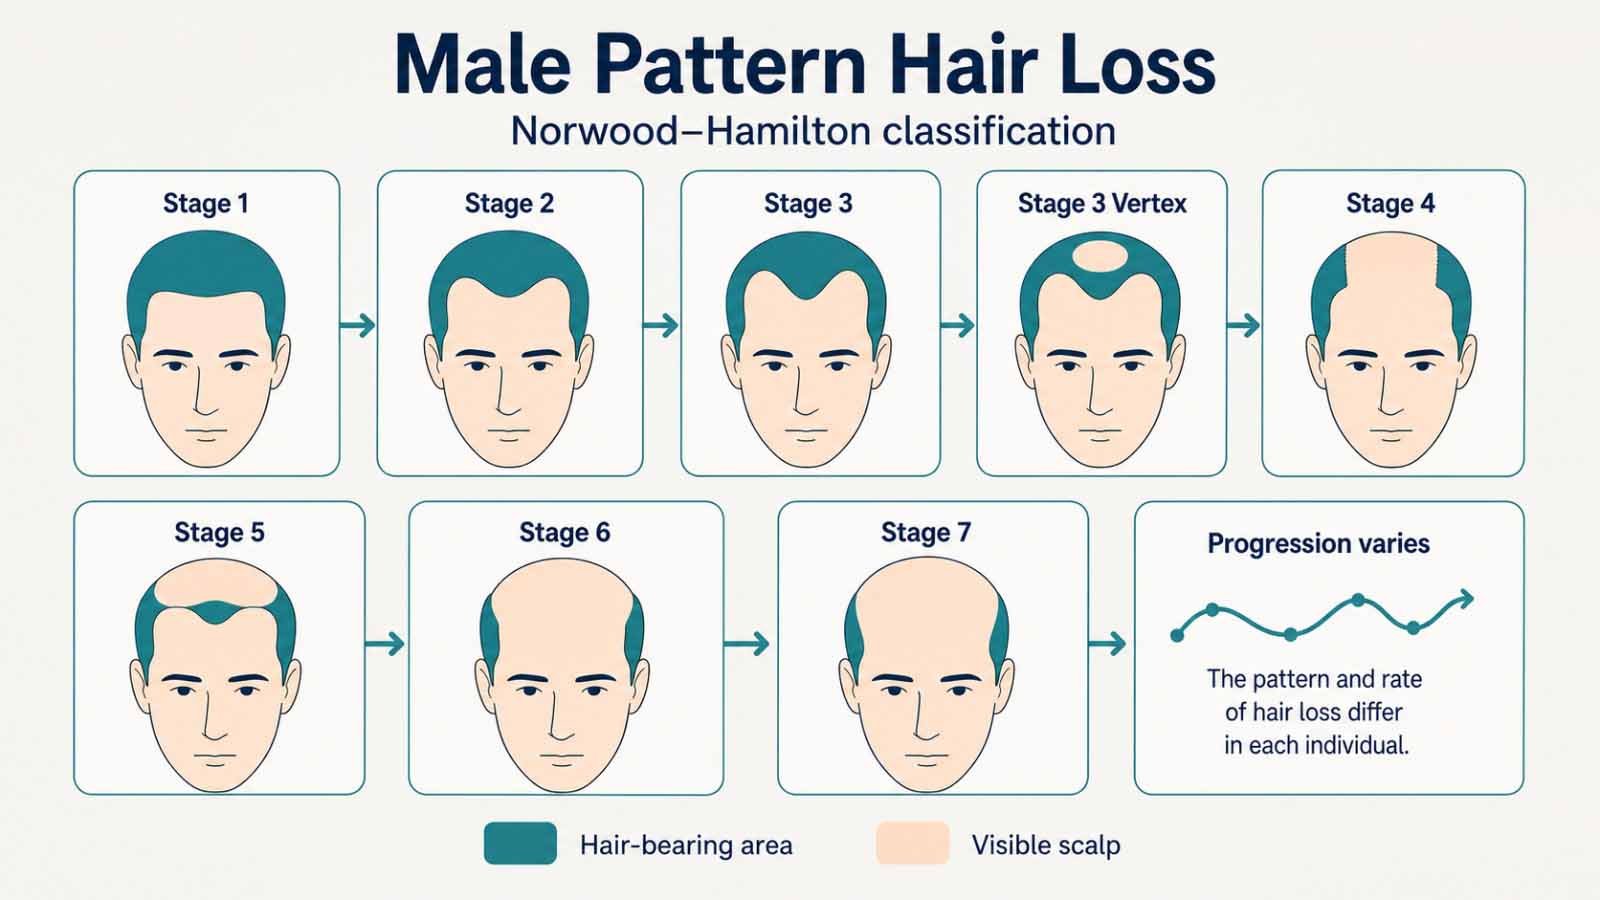
The frontal and vertex scalp are relatively androgen-sensitive. MPHL therefore typically presents with bitemporal recession, vertex thinning, or both, and can be described with the Norwood–Hamilton scale (Norwood, 1975).
MPHL is polygenic. Genome-wide association research has identified multiple loci associated with male-pattern baldness, and susceptibility may be inherited through either parental line (Heilmann-Heimbach et al., 2017). A family history of early hair loss can be associated with earlier onset or greater severity, but does not determine an individual outcome.
Diagnosis is principally clinical and may consider:
The rate and extent of progression vary substantially between individuals.
Not all hair loss in men is androgenetic alopecia. Assessment may need to consider:
Do not stop prescribed medication without medical advice.
A hair-loss consultation may include:
Establishing the diagnosis matters because management differs across the various causes of hair loss.
Contact via WhatsAppThe following describes potential approaches and the evidence base relevant to MPHL. Suitability, expected benefit, risks, and the need for medical supervision differ between individuals. No intervention guarantees a particular outcome.
Appropriate scalp cleansing may support management of sebum, scale, and concurrent scalp inflammation. It is not, by itself, a treatment for androgenetic alopecia.
Low-level laser therapy (LLLT) uses red-light wavelengths, commonly around 630–660 nm. Proposed actions include photobiomodulation within the follicle and changes in cellular signalling. Randomised sham-controlled research has reported improvements in hair-related outcomes in pattern hair loss, although responses and durability vary (Avci et al., 2014; Jimenez et al., 2014).
Tricopat is a device-based scalp-treatment platform that combines controlled superficial skin patting or microdermal stimulation with pressure-wave and iontophoresis-based delivery; protocols may also include red LED exposure. Its proposed roles are to facilitate local delivery of an applied formulation and to provide mechanical/electronic stimulation of the scalp.
In an open-label, non-randomised, single-centre study, Alessandrini and colleagues treated 60 people with androgenetic alopecia, including some women with associated telogen effluvium, with four sessions of preformed growth factors delivered after microdermal stimulation and iontophoresis at three-week intervals. Global photography and trichoscopy improved during follow-up; among the 30 male participants, anterior hair density increased by 14.61% and vertex shaft diameter by 13.62% at six months. All participants completed treatment, and no serious adverse effects were reported (Alessandrini et al., 2021).
Accordingly, Tricopat may be discussed as an adjunctive, device-assisted approach rather than a replacement for evidence-based medical management.
Finasteride is an oral 5-alpha reductase inhibitor that reduces conversion of testosterone to DHT. Randomised trials and systematic-review evidence have reported improvement or stabilisation of hair loss in men with androgenetic alopecia during treatment (Kaufman et al., 1998; Mella et al., 2010). It is a prescription medicine. Potential sexual, mood-related, and other adverse effects should be reviewed with a registered medical practitioner. Benefit is generally dependent on continued treatment.
Topical minoxidil is used to support anagen-phase activity and follicular growth. A randomised clinical trial reported greater hair-count improvement with 5% topical minoxidil than with 2% minoxidil or placebo in men with androgenetic alopecia (Olsen et al., 2002). Potential adverse effects and contraindications require medical assessment, and benefits generally depend on ongoing use.
Hair transplantation relocates follicular units, usually from the occipital donor area, to areas of thinning. Suitability and outcome depend on donor supply, the extent and future trajectory of hair loss, recipient-site characteristics, surgical technique, and individual healing. Risks include bleeding, infection, scarring, and variable graft survival, which should be addressed in pre-operative consultation.
Scalp micropigmentation (SMP) is a cosmetic camouflage procedure in which pigment is placed in the superficial scalp dermis to create the appearance of follicular stippling or greater visual density. It does not regrow hair. It may be considered for selected patients, including scar camouflage or advanced hair loss when surgical donor supply is limited.
Personalised care combining assessment, appropriate investigations, scalp care, and lifestyle guidance to support long-term scalp health and address early hair thinning or shedding.
If you are concerned about hair loss, consult a registered medical practitioner for assessment. This page is for general education only and does not constitute medical advice, diagnosis, or a treatment recommendation. No treatment described here guarantees a specific result.
This page is intended for general educational purposes only. It does not constitute medical advice, diagnosis, or treatment recommendation, and does not create a doctor–patient relationship. For assessment of your individual condition, please consult a registered medical practitioner.